Search the Library
NOTE: This is a new search platform (as of May 2026). If you do a search and don’t get the results you were expecting, please email us at ctnlib@uw.edu to let us know? (If possible, please share your exact search strategy. Thank you!)
Enter keywords and hit Enter (or click the magnifying glass) to search. You can then also select document type or subject/topic to narrow results further (or just use those for searching without a keyword). Results display below this search form.
Document types
Subjects
- CTN-#### format for protocols (CTN-0001, e.g.)
- “exact phrase” (if phrase is not found, it will return results that contain all terms
- word1 NOT word2
- word1 word2 (finds both words)
- Click title to access full-text
- “Show details” reveals abstract & other info
- Checkboxes select items for copy/pasting or printing
- Need help getting a copy of a journal article?
Email ctnlib@uw.edu
Search results

Background: Cannabis is the most commonly used drug in the United States, and among people who use cannabis, polysubstance use is common and understudied. We aimed to examine the association of tetrahydrocannabinol (THC) positive urine drug screen (+UDS) with the odds of submitting a cocaine + UDS during cocaine use disorder treatment.
Methods: We conducted a secondary data analysis of a previously reported double-blind, placebo-controlled clinical trial, CTN0048. Participants meeting criteria for opioid abuse/dependence were assigned to receive extended-release naltrexone and one of three conditions of buprenorphine (placebo, 4 mg/day, 16 mg/day) for 8 weeks. Generalized estimating equations (GEE) were used to analyze urine samples (Liu et al., 2018) collected over time, examining the association between THC + UDS and cocaine + UDS during treatment.
Results: Participants (n = 301) averaged 46 (SD = 8.64) years of age, were majority male (78.41 %), non-Hispanic (89.70 %), and African American (66.45 %). GEE results indicated that patients who submitted THC + UDS had significantly higher odds of submitting cocaine + UDS compared to participants who submitted THC-negative UDS across the 25 time points examined (OR = 1.47, 95 % CI = 1.21–1.79, p = 0.00). Time (OR = 0.9998, 95 % CI: 0.9997, 0.9999, p = 0.018) and the covariate of sex assigned at birth (OR = 1.77, 95 % CI = 1.13–2.77, p = 0.013) were also significant in the model, indicating very small decreases in the odds of submitting a cocaine + UDS over time for all patients and 77 % higher odds of submitting cocaine + UDS for females.
Conclusion: THC + UDS was associated with increased odds of submitting a cocaine + UDS during treatment. Further investigation is needed to discern whether decreasing THC use will result in reduced cocaine use; however, these results suggest that it may be beneficial to counsel patients on cannabis use cessation both before and during treatment for cocaine use, as it is related to cocaine use treatment outcomes.
Related protocols: CTN-0048
In this session, Kathleen T. Brady, MD, PhD, of the Medical University of South Carolina, will discuss the NIDA Clinical Trials Network (CTN) study CTN-0108, “Transcranial Magnetic Stimulation for the Treatment of Methamphetamine/Cocaine Use Disorder,” a pilot study that aims to determine the feasibility, effectiveness, and safety for 20 sessions of repetitive transcranial magnetic stimulation (rTMS) versus sham in adults with a diagnosed methamphetamine or cocaine use disorder. Dr. Brady, co-Principal Investigator for CTN-0108, presented the rationale for the study, including the literature supporting the use of rTMS in stimulant use disorder, as well as the study methodology and preliminary results.
Related protocols: CTN-0108

Aims: This study aimed to examine within and between effects of the relationship between depression, using the Beck Depression Inventory (BDI), and cocaine craving, using the visual analog craving scale (VAS), over time.
Methods: Data from the NIDA Clinical Trial Network Study Cocaine Use Reduction with Buprenorphine (CTN-0048) were used in a secondary analysis (CTN-0148). Random-effects regression modelling was used to examine relationships between participants’ depressive symptoms and their cocaine craving over time.
Results: A total of 301 participants with past-year DSM-IV criteria for cocaine and opioid use disorder were analyzed (21.6% female, 10.3% Hispanic, 66.4% Black) being treated with placebo or buprenorphine+naloxone. Craving significantly decreased over time (B = −1.11, 95% CI [-1.21, −1.02], p < 0.001). Depression emerged as a significant within-person predictor of craving over time (B = 0.93, 95% CI [0.76, 1.09], p<0.001), indicating that when a person’s BDI score increased by one point from their own mean, their craving increased by 0.71 units. Between-person differences in average BDI did not have significant effects (p>0.05), indicating that depression scores across participants did not significantly predict differences in craving.
Conclusions: These findings highlight depression as a dynamic, time-varying clinical marker of heightened craving risk and suggest that monitoring and addressing increases in depressive symptoms during treatment may help mitigate craving spikes and potentially reduce vulnerability in returning to use.
Related protocols: CTN-0148

Cocaine use disorder (CUD) is a major public health issue, and greater cocaine use severity has been associated with worse treatment retention and outcomes. Therefore, greater understanding of processes that influence cocaine use is needed. Both anhedonia (i.e., undervaluation of nondrug rewards) and cocaine demand (i.e., cocaine valuation) are related to cocaine use severity and thematically related to each other at face value, but no studies have directly compared these outcomes to our knowledge.
The present study represents a secondary analysis from a two-phase sequential, multiple assignment, randomized trial aimed at developing adaptive interventions for CUD (CTN-0130). We examined the relationship between anhedonia and cocaine demand and how these measures were related to cocaine use severity. Participants (N = 116) were treatment-seeking adults with CUD. All measures were taken at baseline before treatment initiation. Analyses revealed (a) moderate and very strong evidence of relationships between cocaine demand factors (i.e., persistence, amplitude) and anhedonia (PP values ≥ 77.8%); (b) positive association between cocaine demand (both persistence and amplitude) and measures of cocaine use severity, with the exception of one relationship, which was in the opposite direction; and (c) demand amplitude continued to be positively related to cocaine use severity, even when considering anhedonia.
Conclusions: Overall, findings from this study indicate cocaine demand relates to cocaine use severity more strongly than anhedonia.
Related protocols: CTN-0130
This is the Primary Outcomes Article for CTN-0130.
Fentanyl-related, cocaine-overdose deaths have drastically increased, yet research on how people who use cocaine perceive fentanyl adulteration is limited. This study developed the novel Adulterated Cocaine Purchasing Task, a modification of the original Cocaine Purchasing Task, to quantify how people respond to fentanyl adulteration in cocaine.
In the Adulterated Cocaine Purchasing Task, participants indicated how much cocaine they would purchase when cocaine had no (0%) versus some (10%) probability of fentanyl adulteration. Study aims were to (a) determine how possible fentanyl adulteration affects cocaine demand and (b) determine which individual characteristics predict continued demand for cocaine despite fentanyl adulteration.
This Amazon Mechanical Turk study included self-reported cocaine purchasers (N = 64), who completed self-report questionnaires (demographics, substance use history, depression/posttraumatic stress disorder symptoms, fentanyl knowledge quiz), and the Adulterated Cocaine Purchasing Task.
Results showed (a) that a greater probability of fentanyl adulteration (10%) lowered cocaine demand, but only for intensity (Q₀; amount of cocaine consumed when free; p < .001); (b) no effect on other demand indices (Omax, Pmax, essential value, breakpoint); (c) significantly more zero responders with 10% probability of fentanyl adulteration than 0%, p < .001; and (d) that opioid co-use, depression, age, posttraumatic stress disorder, fentanyl knowledge, and cocaine use severity did not moderate the relationship between fentanyl adulteration and intensity.
Conclusions: Overall, fentanyl adulteration reduced cocaine demand but only for volume preferred at minimal cost, not general motivational drive for use, illustrating the dangerous insensitivity to toxic contamination. The internal validity of the paradigm provides proof-of-concept for this approach to identify individuals at risk from fentanyl-adulterated cocaine.
Related protocols: CTN-0130

Introduction: Despite rising concern about overdoses from fentanyl-adulterated cocaine, research on responses to adulteration among people who use cocaine (PWUC) is limited. We aimed to identify what risk mitigation strategies PWUC would engage in if they suspected fentanyl in their cocaine. Secondarily, we tested whether key individual differences were related to use of risk mitigation strategies.
Methods: A secondary analysis of an online study (CTN Protocol ID: CTN-0130) collected responses from 97 self-reported cocaine purchasers. Participants completed questionnaires on demographics and substance use and reported what they would do if they found out their cocaine might contain fentanyl. Participants selected from a list of behaviors (with a free response option). Responses were coded into a four-level variable: “no change,” “transfer risk,” “harm reduction,” and “abstain.”
Results: About 16.5% endorsed no change in their behavior, 14.4% endorsed transfer risk, 25.8% endorsed harm reduction, and 43.3% endorsed abstain. Of the 10 individual differences tested only cocaine use frequency and previous personal experience of overdose significantly related to selected behaviors. Further analysis showed those with more frequent cocaine use, or prior overdose experience were more likely to use cocaine normally or transfer risk rather than use harm reduction or abstain.
Conclusion: While 83.5% of our sample reported they would attempt to mitigate risk if they suspected fentanyl in their cocaine, participants with more frequent cocaine use or a prior overdose endorsed less use of typical harm reduction or abstention. This highlights the need to direct harm reduction interventions to PWUC to mitigate the fentanyl overdose risks.
Related protocols: CTN-0130
 Background and aims: Despite similar substance use levels, Black adults experience greater family, legal, employment and other social-contextual challenges related to recovery than other groups. Substance use treatments that address both substance use and social-contextual factors are uniquely positioned to address these substance-related problems and produce more sustainable improvements in social functioning than treatment as usual (TAU) or behavioral controls (Control). The aim of this study was to evaluate changes in substance-related problems among Black adults, focusing on the comparative effectiveness between social-contextual treatments and TAU/Control.
Design: Individual-level data synthesis based on secondary analysis of Black adults enrolled in the National Institute on Drug Abuse (NIDA) Clinical Trials Network (CTN).
Setting: All data were collected in the primary studies between 2001 and 2008 at clinics across the United States.
Participants: Black adults who reported cocaine and/or opioid use across nine studies within the NIDA CTN. The sample used herein consisted of individuals from five of these studies who provided data on substance-related problems (n=532; mean age=39.34; standard deviation=9.6).
Measurements: There were two treatment conditions: Social-contextual (e.g. Motivational Interviewing, Seeking Safety, STAGE 12) and TAU/Control. Moderated nonlinear factor analysis estimated latent scores for substance-related problems, using subscales from the Addiction Severity Index, while accounting for measurement noninvariance across studies, time and covariates. Linear mixed models estimated latent score differences over time between social-contextual treatments and TAU/Control during treatment and from the end of treatment through 12-month follow-up.
Findings: Both treatment groups improved across substance-related problem areas from baseline to the end-of-treatment (Cohen’s d = -0.10 to d = -0.47), with effects maintained at 12-month follow-up. Although social-contextual treatments did not statistically significantly outperform TAU/Control from baseline to end-of-treatment, they showed greater effects from end of treatment to 12-month follow-up in family/social [Cohen’s d difference ( d) = -0.47, 95% confidence interval (CI) = -0.57 to -0.38], legal ( d = -0.20, 95% CI = -0.31 to -0.10) and psychiatric problems ( d = 0.29, 95% CI = -0.38 to -0.20) than TAU/Control. Sensitivity analyses indicated that Seeking Safety and STAGE 12 predominantly drove post-treatment improvements in family/social problems.
Conclusions: Substance use treatment may yield broader, delayed benefits beyond substance use reduction among Black adults in the United States. Compared with treatment-as-usual, social-contextual treatments can yield more sustainable effects in legal, family and psychiatric areas among Black adults, with interventions such as Seeking Safety and STAGE 12 showing particular benefits in addressing family-related challenges.
Related protocols: CTN-0125
 Background: Patient-perceived Quality-of-Life (QOL) and treatment effectiveness (TEA) have previously been shown to be positively associated with better substance use treatment outcomes.
Objectives: This study examined potentially causal relationships amongst QOL, TEA, and cocaine abstinence.
Methods: Secondary data analyses (CTN-0148) were conducted on the NIDA Clinical Trial Network study, Cocaine Use Reduction with Buprenorphine (CTN-0048). N = 301 participants with DSM-IV cocaine dependence and opioid use history were administered injectable naltrexone and randomized to one of three buprenorphine/naloxone doses, 4 mg/1 mg, 16 mg/4 mg or placebo. Mediation models estimated direct and indirect effects amongst QOL, TEA, and cocaine abstinence.
Results: The QOL Environment domain exerted a significant indirect effect (B=0.01, SE=0.01, 95% CI=[0.00, 0.02]) on cocaine abstinence and a direct effect on TEA (B=0.57, SE=0.22, 95% CI=[0.16, 1.01]). Other QOL domains and individual QOL items exerted no statistically significant direct effects on cocaine abstinence. Overall QOL exerted a significant direct effect on TEA (95% CI=[0.32, 2.45]) along with a significant indirect effect on cocaine abstinence (95% CI=[0.01, 0.05]). TEA had a significant positive direct effect on cocaine abstinence (95% CI=[0.01, 0.02]).
Conclusion: Overall QOL and environmental QOL are related to treatment response through their relationship with patients’ perception of treatment effectiveness. TEA is directly related to cocaine abstinence at the end of treatment. QOL and TEA measures may serve as indicators of a need for additional support within care plans. These findings highlight the impact of a patient’s sense of well-being and their perceived treatment effectiveness on biochemically validated cocaine abstinence.
Related protocols: CTN-0148
 Background: Cocaine remains the most abused stimulant, causing considerable morbidity and mortality. Despite decades of research, there is no FDA-approved medication to treat cocaine use disorder (CUD). In individuals with cocaine and opioid dependence/abuse, extended-release injectable naltrexone (XR-NTX) and sublingual buprenorphine (BUP; 16 mg with naloxone; Suboxone) reduced cocaine use compared to placebo and XR-NTX in the “Cocaine Use Reduction with Buprenorphine” (CURB; CTN-0048) study.
Objectives: The CURB-2 (CTN-0109) study aims to examine whether administering XR-NTX in combination with extended-release injectable buprenorphine (XR-BUP), thus creating a “kappa antagonist,” is an effective pharmacotherapy compared to placebo for the treatment of CUD.
Study design: CURB-2 is a fully powered, phase IIb, randomized, placebo-controlled trial. Approximately 426 participants will be randomized across 12 study sites in the United States. There will be a 1-week medication induction phase, an 8-week active medication phase, and a 4-week follow-up phase. XR-NTX (Day 1, Week 3, Week 6) will be administered before XR-BUP (Day 4, Week 4). With naltrexone blocking the mu-opioid receptors, the reinforcing effects of buprenorphine will be blocked while leaving the kappa antagonist effects.
Discussion: If this kappa antagonist approach demonstrates efficacy in reducing urine-verified cocaine use compared to placebo, XR-NTX and XR-BUP combination therapy would be an important tool in addressing cocaine use disorder.
Related protocols: CTN-0109
 Background: Cocaine and methamphetamine use disorders (CcUD/MtUD) have serious public health, medical, and psychiatric consequences. Yet, there are no U.S. Food and Drug Administration (FDA) approved treatments available. The STIMULUS study is a multi-site trial, sponsored by NIDA’s National Drug Abuse Treatment Clinical Trials Network (CTN), that aims to investigate the feasibility and preliminary efficacy of repetitive transcranial magnetic stimulation (rTMS) as a potential treatment for moderate to severe CcUD/MtUD.
Methods: The study is a double-blind, sham-controlled trial seeking to recruit 160 participants with a current moderate to severe CcUD or MtUD diagnosis, randomized to receive active rTMS (10-Hz stimulation at 120% motor threshold over the left dorsolateral prefrontal cortex) or sham. Feasibility is assessed by a target of at least 20 treatment sessions administered within an 8-week period. Additionally, the study aims to evaluate the efficacy of rTMS in reducing stimulant use and craving, the impact of rTMS on mood, anxiety, sleep, and other measures, and the utility of electroencephalography as a treatment response biomarker.
Discussion: Studies exploring rTMS for stimulant use disorders remain limited by small sample sizes, as well as great heterogeneity in defined study population, treatment parameters, retention in treatment, and number of sessions. In this paper, we highlight key study design decisions, such as safety, sham procedure, and schedule flexibility.
Conclusions:
We hope that the data collected will lay the groundwork for a robust randomized controlled trial of rTMS as a therapeutic intervention for individuals with CcUD/MtUD.
Related protocols: CTN-0108
This is the Primary Outcomes Article for CTN-0125.
Cocaine- and opioid-related overdose deaths have increased among Black people, which makes identifying effective treatments for Black people a high priority. We investigated the comparative effectiveness of behavioral treatments among Black adults who use cocaine and/or opioids.
Methods: Identified multisite randomized clinical trials (RCTs) of behavioral interventions that targeted substance use, had participants who self-identified as Black, and included cocaine use outcome measures from the National Drug Abuse Treatment Clinical Trials Network (CTN) datashare. We estimated cocaine use and opioid use severity scale scores while considering study-level measurement non-invariance. Then, we estimated the inverse probability of treatment-weighted (IPTW) linear mixed models to assess comparative effectiveness of treatments that address social-contextual factors and those focused solely on substance use (e.g., contingency management (CM)) relative to treatment-as-usual/controls on cocaine use and opioid use severity scores during- and post-treatment.
Results: Nine RCTs met inclusion criteria, with a combined sample of 1,381 Black adults who used cocaine and/or opioids. The IPTW linear mixed models indicated that cocaine use severity decreased from baseline to end-of-treatment across three treatment groups, with a greater decrease for social-contextual treatments and CM relative to treatment-as-usual/controls. However, this greater reduction was maintained at 12-month follow-ups for social-contextual treatments, while CM worsened relative to TAU/controls. We found decreases in latent opioid use severity with no or minor differences between treatment groups.
Conclusions: The findings suggest that addressing social-contextual factors is an essential treatment component for long-term reduction of cocaine use among Black adults.
Related protocols: CTN-0125
 The Treatment Effectiveness Assessment (TEA) score is derived from a 4-item self-administered assessment utilizing a Likert scale to evaluate changes across four life domains: substance use, personal responsibilities, health, and citizenship. The World Health Organization Quality of Life Brief (WHOQOL-BREF) scale is a shortened version of the original instrument that may be more convenient for use in large research studies or clinical trials. It assesses the individual’s perceptions in the context of their culture and value systems, and their personal goals, standards, and concerns. Cocaine craving is a core symptom of cocaine use disorder and remains a consistent obstacle to achieving sustained reductions in use and relapse prevention.
This secondary analysis of data from CTN-0048 aimed to examine relationships between quality of life and health satisfaction (using the WHO-QOL scale), cocaine use (urine drug screens), and patient ratings of treatment effectiveness, as measured by the TEA over 8 weeks of treatment.
Results found significant negative relationships between cocaine craving and TEA and significant positive relationships between patient quality of life and satisfaction with health. A model including 4 health domains also indicated that there were significant positive relationships between health domains and TEA as well. TEA was not significantly related to longest duration of abstinence (LDA) for cocaine verified by urine drug screens.
Conclusions: Self-reported treatment effectiveness was integrally related to patient level factors, over time, while in treatment for cocaine use disorder and receiving placebo or buprenorphine and extended-release naltrexone, however TEA was not predictive of LDA. Recognizing and providing parallel intervention for these patient level factors during substance use disorder treatment may enhance patient reports of treatment effectiveness, indicating improvement across the patient reported domains of substance use, life satisfaction, health, and community.
Related protocols: CTN-0048
 Stimulants are the drivers of the fourth wave of the United States drug overdose epidemic. Kappa opioid receptor antagonists promote feelings of wellbeing and represent a medication addressing the “dark side.” In a pilot study, extended-release naltrexone (XR-NTX) plus oral buprenorphine (BUP), 4mg and 16mg, produced modest, though statistically significant, reductions in cocaine use among those adherent to oral BUP compared to placebo. This presentation describes CTN-0110, a study designed to test monotherapy for buprenorphine as the medication is used for treatment of refractory depression in people with no opioid use disorder (OUD).
Related protocols: CTN-0110
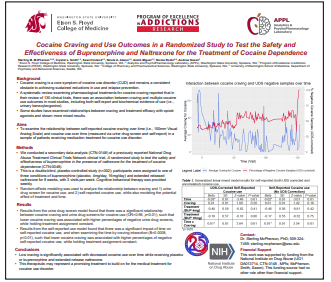 Cocaine craving is a core symptom of cocaine use disorder (CUD) and remains a consistent obstacle to achieving sustained reductions in use and relapse prevention. A systematic review examining pharmacological treatment for cocaine craving reported that in their review of 130 clinical trials, there was an association between craving and multiple cocaine use outcomes in most studies, including both self-report and biochemical evidence of use (i.e., urinary benzoylecgonine). Some studies have examined relationships between craving and treatment efficacy with opioid agonists and shown more mixed results.
This study aimed to examine the relationship between self-reported cocaine craving over time (i.e., 100mm Visual Analog Scale) and cocaine use over time (measured via urine drug screen and self-report) in a sample of patients receiving medication treatment for cocaine use disorder (from CTN-0148).
Results from the urine drug screen model found that there was a significant relationship between cocaine craving and urine drug screens for cocaine use (OR=0.98, p<0.01), such that lower cocaine craving was associated with higher percentages of negative urine drug screens, while holding treatment assignment constant. Results from the self-reported use model found that there was a significant impact of time on self-reported cocaine use, and when examining the time by craving interaction (B=0.0008, p<0.01), such that lower cocaine craving was associated with higher percentages of negative self-reported cocaine use, while holding treatment assignment constant.
Conclusions: Low craving is significantly associated with decreased cocaine use over time while receiving placebo or buprenorphine and extended-release naltrexone. This therapeutic may represent a promising treatment to build on for the medical treatment for cocaine use disorder.
Related protocols: CTN-0148
 Polysubstance use may complicate treatment outcomes for individuals who use opioids. This research aimed to examine the prevalence of polysubstance use in an opioid use disorder treatment trial population and polysubstance use’s association with opioid relapse and craving.
This study is a secondary data analysis of individuals with opioid use disorder who received at least one dose of medication (n=474) as part of a 24-week, multi-site, open label, randomized Clinical Trials Network study (CTN-0051, X:BOT) comparing the effectiveness of extended-release naltrexone versus buprenorphine. Models examined pretreatment polysubstance use and polysubstance use during the initial 4 weeks of treatment on outcomes of relapse by week 24 of the treatment trial and opioid craving.
Polysubstance use was generally not associated with treatment outcomes of opioid relapse and craving. Proportion of days of pretreatment sedative use was associated with increased likelihood of opioid relapse (OR: 1.01, 95% CI: 1.00–1.02). Proportion of days of cocaine use during the initial 4 weeks of treatment was associated with increased likelihood of opioid relapse (OR: 1.05, 95% CI: 1.01–1.09) but this effect was no longer significant once the potential of confounding by opioid use was considered. Sedative use during initial 4 weeks of treatment was associated with increased opioid craving (b: 0.77, 95% CI: 0.01–1.52). The study found no other significant relationships.
Conclusions: In the current study population, polysubstance use was only marginally associated with 24-week treatment outcomes.
Related protocols: CTN-0051