Search the Library
NOTE: This is a new search platform (as of May 2026). If you do a search and don’t get the results you were expecting, please email us at ctnlib@uw.edu to let us know? (If possible, please share your exact search strategy. Thank you!)
Enter keywords and hit Enter (or click the magnifying glass) to search. You can then also select document type or subject/topic to narrow results further (or just use those for searching without a keyword). Results display below this search form.
Document types
Subjects
- CTN-#### format for protocols (CTN-0001, e.g.)
- “exact phrase” (if phrase is not found, it will return results that contain all terms
- word1 NOT word2
- word1 word2 (finds both words)
- Click title to access full-text
- “Show details” reveals abstract & other info
- Checkboxes select items for copy/pasting or printing
- Need help getting a copy of a journal article?
Email ctnlib@uw.edu
Search results

Substance use disorder (SUD) is a complex chronic condition requiring a multi-disciplinary approach to both research and treatment. Randomized controlled trials (RCTs) are gold standard methodologies for inferring causal relationships between an intervention and treatment outcomes but often face challenges in generalizability, scalability and real-world implementation. Target trial emulation (TTE) is a powerful methodological framework that uses observational or real-world data sources to emulate the methodology of these gold standard target trials to complement the learning from RCTs and enhance translation to real world evidence. An additional methodological innovation is the translational testing of clinical- and community-based digital health systems to provide new insights into SUD in the real world and provide scalable access to therapeutic resources.
To explore these methodological innovations in SUD research, the National Institute on Drug Abuse Center for the Clinical Trials Network convened a variety of experts for a virtual workshop titled “Target Trial Emulation in Observational Research and Translational Testing of Advanced Digital Health Tools for Substance Use Disorder Prevention and Treatment.” This article summarizes the discourse of the workshop, focused on three thematic areas: TTE using real-world healthcare data, SUD evidence from nationwide data sources that may be useful in TTE analyses, and translational testing of clinical- and community-based digital health systems. The workshop also highlighted various exemplars of digital health systems that demonstrate success in translational research addressing SUDs, key methodological and translational challenges, importance of rigorous study design, robust data linkages and expanding use of common data elements, and the integration of digital health tools to enhance causal inference and clinical impact. Future research directions are outlined to refine these approaches, address barriers, and maximize the utility of real-world data in shaping effective SUD prevention and treatment strategies.

This presentation provided a brief summary of the CTN-0135 study, Buprenorphine Treatment Engagement and Induction Problems Among Individuals Using Fentanyl, which aimed to determine whether there are regional variations in the prevalence of fentanyl use and problems initiating buprenorphine/naloxone. A secondary purpose was to characterize the specific problems that clinicians are encountering when initiating BUP treatment in patients using fentanyl and to determine how standard clinical protocols are being modified to engage patients in treatment, which was carried out via a survey administered to 396 clinicians.
The study team wanted to explore other dissemination strategies besides publishing in peer-reviewed journals in order to better share the results with a broader audience. To that end, they decided to develop an online data dashboard, which they developed using Shiny Apps. A second survey was sent out to original participants who had opted in for future contact (n=364) to ask questions about the dashboard, including questions about general usability, basic demographics, and some open-ended items.
Responses to the dashboard were positive, with 84.4% reporting they were at least “somewhat satisfied” with the dashboard. 91.7% found the study results to be relevant to clinical practice, and 77.7% said they would be likely to use a data dashboard to learn about study results. Strengths of the dashboard noted in the open-ended questions included “simplicity and ease of use,” while opportunities for improvement included “color scheme, scrolling reduction, and font sizes.”
Overall, the data dashboard evaluation results suggest it is a feasible dissemination strategy for a clinical audience: easy to use, something clinicians would recommend to colleagues, and clinically relevant. Future work should integrate users into the development process and consider visualization literacy as well as computer skills.
Find the Trends in Drug Use Study Dashboard here.
Related protocols: CTN-0135
Given the disproportionate impact of substance use on individuals, families, and communities from populations underrepresented in clinical trials, increasing their enrollment in treatment research is critical for ensuring that the findings inform policies and programs that are inclusive of all communities, thereby advancing health equity. However, since underrepresented groups continue to be underenrolled in clinical trials testing the efficacy and effectiveness of psychosocial treatments for substance use disorder, substance use researchers are still grappling with this challenge.
In this commentary, we describe rigorous methodological approaches, such as integrative data analysis (IDA) and related methods (e.g., moderated nonlinear factor analysis and propensity score weighting), that can help address the challenges posed by the underrepresentation of certain populations. By combining individual-level data from multiple studies into a pooled dataset, these methods increase sample size and statistical power while addressing covariate imbalance across treatment groups. We describe how we employed these methods to address the aims of our recently completed secondary data analysis project conducted within the National Drug Abuse Treatment Clinical Trial Network (CTN-0125; Integrative Data Analysis of CTN Studies to Examine the Impact of Psychosocial Treatments for Black People Who Use Cocaine and/or Opioids). Our study used these methods to pool and analyze data from nine completed CTN trials to assess the comparative effectiveness of psychosocial treatments for Black adults who use cocaine and/or opioids, a group underrepresented in registered trials of the NIDA. We illustrate the application of these methodological approaches in CTN-0125 and demonstrate how they complement each other to address unique analytic challenges. We describe how we addressed data harmonization challenges due to variations in data formats and inconsistencies or gaps in the supportive documentation available on the NIDA Data Share website. We conclude with recommendations for the research field on how to further address sample size and data integration challenges.
Related protocols: CTN-0125
The integration of data across randomized controlled trials (RCTs) testing interventions and treatments for substance use disorder (SUD) offers a rich opportunity for improving the evidence base and analytic methods used in SUD research. With over 50 completed trials of the National Institute on Drug Abuse (NIDA) National Drug Abuse Treatment Clinical Trials Network (CTN) available for secondary analysis and harmonization, the possibilities are extensive, but the effort to harmonize and document datasets demands complex analytic formulation and methodology. This commentary discusses strengths and challenges of data harmonization, sharing clinical and data science considerations based on four exemplar studies that harmonized data across multiple CTN trials. We offer recommendations for others planning data harmonization for secondary analysis, discuss guiding principles for research data management, outline suggestions to bridge gaps in the context of the CTN, and finally frame considerations for using state-of-the-art tools such as generative AI and integration of data from clinical trials and electronic health records to enhance the promise of data harmonization.
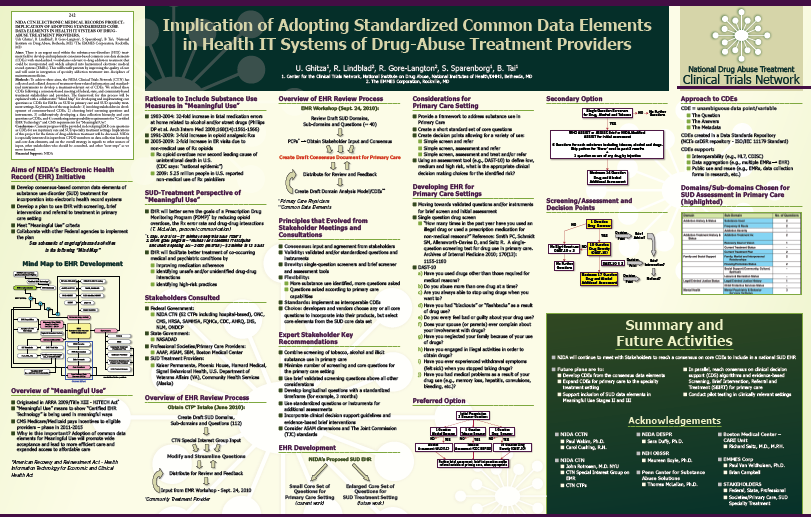 There is an urgent need within the substance-use-disorders (SUD) treatment field to develop and implement consensus-based common core data elements (CDEs) with standardized vocabularies relevant to drug addiction treatment that could be incorporated and widely adopted into harmonized electronic medical record systems (EMRs). This will benefit patients by improving the quality of care and will assist in integration of specialty addiction treatment into disciplines of mainstream medicine. To achieve these aims, the NIDA Clinical Trials Network (CTN) has collected and collated dozens of treatment-form-related information and standardized instruments to develop a treatment-relevant set of CDEs. These CDEs were refined following a consensus-based meeting of federal, state, and community-based treatment stakeholders and providers. This poster describes the collaborative “Mind Map” used for developing and implementing core questions as CDEs for EMRs on SUD in primary care and SUD specialty treatment settings. Current progress in developing EMR core questions as CDEs for use in those settings is also provided, as well as implications of this project for the future of drug abuse treatment. NIDA is especially interested in input from College on Problems of Drug Dependence (CPDD) members on data collection hierarchy and core data elements and on the overall strategy in regards to other sources of input, other stakeholders who should be consulted, and other “next steps” as this project moves forward.
 Several large-scale, pragmatic clinical trials on opioid use disorder (OUD) have been completed in the National Drug Abuse Treatment Clinical Trials Network (CTN). However, the resulting data have not been harmonized between the studies to compare the patient characteristics. This paper provides lessons learned from a large-scale harmonization process that are critical for all biomedical researchers collecting new data and those tasked with combining datasets.
Researchers harmonized data from multiple domains from CTN-0027 (N = 1269), which compared methadone and buprenorphine at federally licensed methadone treatment programs; CTN-0030 (N = 653), which recruited patients who used predominantly prescription opioids and were treated with buprenorphine; and CTN-0051 (N = 570), which compared buprenorphine and extended-release naltrexone (XR-NTX) and recruited from inpatient treatment facilities. Patient-level data were harmonized and a total of 23 database tables, with meticulous documentation, covering more than 110 variables, along with three tables with “meta-data” about the study design and treatment arms, were created. Domains included: social and demographic characteristics, medical and psychiatric history, self-reported drug use details and urine drug screening results, withdrawal, and treatment drug details.
In this paper, the authors summarize the numerous issues with the organization and fidelity of the publicly available data which were noted and resolved, and present results on patient characteristics across the three trials and the harmonized domains, respectively. A systematic harmonization of OUD clinical trial data can be accomplished, despite heterogeneous data coding and classification procedures, by standardizing commonly assessed characteristics. Similar methods, embracing database normalization and/or “tidy” data, should be used for future datasets in other substance use disorder clinical trials.
Related protocols: CTN-0027, CTN-0030, CTN-0051
The efficacy of treatments for substance use disorders (SUD) is tested in clinical trials in which participants typically provide urine samples to detect whether the person has used certain substances via urine drug screenings (UDS). UDS data form the foundation of treatment outcome assessment in the vast majority of SUD clinical trials. However, existing methods to calculate treatment outcomes are not standardized, impeding comparability between studies and prohibiting reproducibility of results.
In this study, the researchers extended the concept of a binary UDS variable to multiple categories: “+” [positive for substance(s) of interest], “–” [negative for substance(s)], “o” [patient failed to provide sample], “*” [inconclusive or mixed results], and “_” [no specimens required per study design]. This construct can be used to create a standardized and sufficient representation of UDS datastreams and sufficiently collapses longitudinal records into a single, compact “word”, which preserves all information contained in the original data.
Researchers developed the R software package CTNote (available on CRAN) as a tool to enable computers to parse these “words”. The software package contains five groups of routines: detect a substance use pattern, account for a specific trial protocol, handle missing UDS data, measure the longest period of consecutive behavior, and count substance use events. Executing permutations of these routines result in algorithms which can define SUD clinical trial endpoints. As examples, the authors provide three algorithms to define primary endpoints from seminal SUD clinical trials
Conclusions: Representing substance use patterns as a “word” allows researchers and clinicians an “at a glance” assessment of participants’ responses to treatment over time. Further, machine readable use pattern summaries are a standardized method to calculate treatment outcomes and are therefore useful to all future SUD clinical trials. The paper includes discussion of some caveats when applying this data summarization technique in practice and areas of future study.
Related protocols: CTN-0094
 The purpose of this study was to estimate how results would have varied if a substance abuse clinical trial had been conducted with nationally representative adults with substance use and with representative adults receiving substance use treatment. Results were analyzed from NIDA Clinical Trials Network protocol CTN-0044, a multisite clinical trial comparing the effectiveness of the Therapeutic Education System to treatment as usual for outpatient addiction treatment (n = 507). Patients were recruited between June 2010 and August 2011. Abstinence was the primary outcome. The general population sample and general population-treated samples were derived from Wave 1 of the National Epidemiologic Survey on Alcohol and Related Conditions (NESARC) (n = 43,093). Propensity scores provided a standardized measure of the difference between clinical trial participants and the 2 NESARC samples. The clinical trial was reanalyzed by reweighting the sample with propensity scores derived from the 2 samples to obtain generalizable estimates of treatment effects.
Before the clinical trial sample was reweighted, the odds ratio (OR) of response to Therapeutic Education System versus treatment as usual in the trial was 1.62 (95% CI, 1.12-2.35). After the sample was reweighted to be representative of the 2 NESARC groups, ORs were 1.33 (95% CI, 0.34-5.26) for the representative sample with any substance use and 1.64 (95% CI, 0.82-3.27) for the representative treated sample. The effect size of the original study was statistically significant; the estimate effect size for the nationally representative sample was not. This does not necessarily mean that the Therapeutic Education System is not efficacious for the treatment of substance use disorders. Instead, the width of the confidence intervals reflects increased uncertainty associated with extrapolating the results of the clinical trial sample to broader populations.
Conclusions: Applying propensity score weighting to clinical trial results provides a method for estimating the population generalizability of clinical trial findings that relies on effect moderators observed in the study sample and population. Broader confidence intervals in the reweighted samples do not necessarily indicate lack of efficacy of the Therapeutic Education System but rather greater uncertainty concerning effectiveness in general population samples.
Related protocols: CTN-0044
This webinar provided an update on CTN-0062-Ot, a phased feasibility and proof-of-concept study seeking to incorporate addiction-specific screening and assessment of common data elements (CDEs) into a widely used electronic health record (EHR), explore the logistics and time required to do this, and assess impacts on the frequency of identification, diagnosis, and referral to treatment in large healthcare organizations.
The webinar included these components (click each title for the individual slides):
- A Phased-Implementation Feasibility and Proof-of-Concept Study to Assess Incorporating the NIDA CTN Common Data Elements into the Electronic Health Record in Large Primary Care Settings (CDE-EHR-PC Study, CTN-0062-Ot). Jennifer McNeely, MD, MS, New York University School of Medicine
- Usability: An Introduction. Joseph Kannry, MD, Mount Sinai Health System
- Usability in Healthcare IT: Data Collection and Analysis Approaches. Andrew Kushniruk, PhD, School of Health Information Science, University of Victoria
- Lessons Learned and Conclusion.
Related protocols: CTN-0062-Ot
The mHealth revolution brings exciting possibilities for both researchers and clinicians, but the use of this technology also raises unique ethical concerns. The purpose of this talk is two-fold. First, we will be discussing some of the most pressing ethical challenges around mHealth. This will involve looking carefully at issues around data ownership, privacy, transparency, and consent. Second, we will introduce some possible solutions. Come discuss what researchers, clinicians, and institutions can do to address ethical risk.
Dr. Tiffany Cvrkel is a bioethicist, philosopher, and lecturer in UCLA’s Department of Molecular, Cell, & Developmental Biology. The primary focus of her work is categorizing the impact and limitations of deliberation as it occurs in the contexts of biomedical ethics. Her particular area of expertise is the ethics of emerging biomedical technologies, including the ethical challenges around mHealth, eHealth, and Big Data. In addition to being an award-winning teacher, she serves as a consultant to scientists and clinicians working with bioethical questions. She specializes in both bringing clarity to bioethical challenges and to assisting in the creation of practical solutions.
Additional Resources:
- Download slides (pdf)
 The National Drug Abuse Treatment Clinical Trials Network (CTN) of the National Institute on Drug Abuse (NIDA) recently launched a public portal which provides a single-source repository for CTN-recommended common data elements (CDEs) for substance use disorders (SUD) for use in electronic health record systems (EHRs) and clinical research. A CDE in this context is a data element consisting of a question and enumerated set of possible values for responses precisely defined by standardized metadata descriptors. CDEs consisting of individual question/answer pairs can be combined into more complex questionnaires and case report forms or used when gathering medical information in the context of providing clinical care. Thus, CDEs describe semantic characteristics for a discrete piece of data, which will be collected, stored, or exchanged during the course of a study or health examination. This will facilitate exchange of standardized data because of the use of CDEs. In this manner, NIDA CDEs can be commonly applied to multiple data collection systems whether in research or clinical care and across different institutions, such that their intentional commonality with use of common data standards can improve data quality, facilitate data repurposing, and promote data sharing.
This paper describes objectives and importance of the CTN CDEs initiative and portal to translational psychiatric research: To support harmonized use of EHR-compatible common data elements to enable exchange and integration of data to answer clinical meaningful questions of broad interest to SUD treatment research, thereby facilitating big-data biomedical science crossing boundaries between research and clinical care.
 The purpose of this study was to examine sensitivity to missing data procedures on treatment effects in a randomized controlled trial (RCT) of osmotic-release methylphenidate (OROS) for adolescents with co-occurring attention-deficit/hyperactivity disorder (ADHD) and substance use disorders (SUD). Data came from a National Drug Abuse Treatment Clinical Trials Network study (CTN-0028, N=303), which evaluated the safety/efficacy of a 16-week RCT of OROS vs. placebo in adolescents aged 13-18 with ADHD who were also receiving cognitive-behavioral therapy for their SUD. The two primary outcomes were clinician-reported ADHD symptoms and self-reported past 28 days of substance use (SU). A parallel grow model was used to assess the effect sizes assuming missing at random (MAR) compared to two missing not at random (MNAR) models: Diggle-Kenward (DK) selection model and Wu-Carroll (WC) selection model.
The MAR model found no significant treatment effect on ADHD or SU, and the effect sizes were small for both ADHD and SU. The MNAR DK model also produced non-significant treatment effects with similar effect sizes of ADHD and SU. The MNAR WC model evidenced a significant effect of OROS relative to placebo on SU, and the effect sizes for both ADHD and SU were larger than reported in the other models.
Conclusions: While the MAR model and one MNAR model found similarly sized effects as the original RCT, the second MNAR model produced different results for both of the outcomes. This sensitivity analysis highlights an important need for future RCTs of co-morbid mental illness and SUDs to carefully evaluate the missing data assumptions made when assessing treatment effects.
Related protocols: CTN-0028
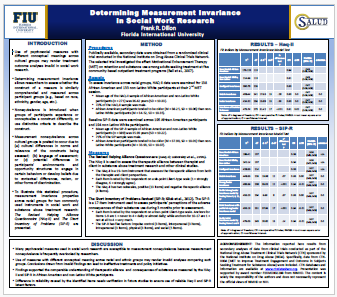 Use of psychosocial measures with different conceptual meanings across cultural groups may render treatment outcome analyses invalid in social work research. Determining measurement invariance allows researchers to assess whether the construct of a measure is similarly comprehended and measured across participant groups (e.g., based on race, ethnicity, gender, age, etc.). Nonequivalence is introduced when groups of participants experience or conceptualize a construct differently, or use distinctive criteria to describe the concept. Measurement nonequivalence across cultural groups is posited to occur due to (a) cultural differences in norms and relevance of the constructs being assessed; (b) language of assessment; or (c) potential differences in participants’ environments and opportunity structures to engage in certain behaviors or develop beliefs due to contextual differences, racism, or other forms of discrimination.
To illustrate this statistical procedure, this poster presents measurement invariance properties across racial groups for two commonly used instruments in social work and substance abuse treatment research (the Revised Helping Alliance Questionnaire (HAq-II) and the Short Inventory of Problems (SIP-R)), using data from the National Drug Abuse Treatment Clinical Trials Network protocol CTN-0004 (“Motivational Enhancement Treatment to Improve Treatment Engagement and Outcome in Subjects Seeking Treatment for Substance Abuse”). Analysis shows that use of measures with different conceptual meaning across racial and ethnic groups may render invalid analyses comparing such groups. Conclusions drawn from invalid findings can lead to ineffective treatments and policy initiatives.
Conclusions: Findings support the comparable understanding of therapeutic alliance and consequences of substance as measured by the HAq-II and SIP-R in African American and non-Latino white participants. Difference in reliability caused by the identified items needs verification in future studies to ensure use of reliable HAq-II and SIP-R latent factors.
Related protocols: CTN-0004
 There are many benefits of data sharing, including the promotion of new research from effective use of existing data, replication of findings through re-analysis of pooled data files, meta-analysis using individual patient data, and reinforcement of open scientific inquiry. A randomized controlled trial is considered the “gold standard” for establishing treatment effectiveness, but clinical trial research is very costly — sharing data is an opportunity to expand the investment of the clinical trial beyond its original goals at minimal cost. This article describes the goals, developments, and usage of the Data Share website for the National Drug Abuse Treatment Clinical Trials Network (CTN) in the U.S., including lessons learned, limitations, and major revisions, and considerations for future directions to improve data sharing. Since its inception in 2006 and through October 2012, nearly 1700 downloads from 27 clinical trials have been accessed from the Data Share website, with use increasing over the years. Individuals from 31 countries have downloaded data from the site, and there have been at least 13 publications derived from analysis of data obtained through the public Data Share website. Limitations of the website include minimal control over data requests and usage, which has resulted in little information and lack of control regarding how the data from the website are being used, and a lack of uniformity in data elements collected across CTN trials, which has limited cross-study analyses.
Conclusions: The Data Share website offers researchers easy access to de-identified data files with the goal to promote additional research and identify new findings from completed CTN studies. To maximize the utility of the website, ongoing collaborative efforts are needed to standardize the core measures used for data collection in the CTN studies with the goal of increasing their comparability and facilitating the ability to pool data files for cross-study analyses.
Supported by the Duke Clinical Research Institute (CTN DSC 1).
 A review of substance use clinical trials indicates that sub-optimal methods are the most commonly used procedures to deal with longitudinal missing information. In this study of data from the National Drug Abuse Treatment Clinical Trials Network buprenorphine protocol CTN-0003, listwise deletion (i.e., using complete cases only), positive urine analysis (UA) imputation, and multiple imputation (MI) were used to evaluate the effect of baseline substance use and buprenorphine/naloxone tapering schedule (7 or 28 days) on the probability of a positive UA (UA+) across the 4-week treatment period. The listwise deletion generalized estimating equations (GEE) model demonstrated that those in the 28-day taper group were less likely to submit a UA+ for opioids during the treatment period, as did the positive UA imputation model. The MI model also demonstrated a similar effect of taper group, but the effect size was more similar to that of the listwise deletion model.
Conclusions: The missing data situation described in this investigation generalizes to many other substance use psychopharmacology clinical trials wherein there is missing data on the outcome of interest only. Future researchers may find utilization of the MI procedure in conjunction with the common method of GEE analysis as a helpful analytic approach when the missing at random assumption is justifiable.
Related protocols: CTN-0003