Search the Library
NOTE: This is a new search platform (as of May 2026). If you do a search and don’t get the results you were expecting, please email us at ctnlib@uw.edu to let us know? (If possible, please share your exact search strategy. Thank you!)
Enter keywords and hit Enter (or click the magnifying glass) to search. You can then also select document type or subject/topic to narrow results further (or just use those for searching without a keyword). Results display below this search form.
Document types
Subjects
- CTN-#### format for protocols (CTN-0001, e.g.)
- “exact phrase” (if phrase is not found, it will return results that contain all terms
- word1 NOT word2
- word1 word2 (finds both words)
- Click title to access full-text
- “Show details” reveals abstract & other info
- Checkboxes select items for copy/pasting or printing
- Need help getting a copy of a journal article?
Email ctnlib@uw.edu
Search results
In this session, Drs. Rossom and Hooker discussed the design and implementation of Opioid Wizard, a clinical decision support tool embedded in the EHR for primary care clinicians and developed as part of NIDA Clinical Trials Network protocol CTN-0095. The goal of the tool is to help clinicians identify, screen, diagnose and treat opioid use disorder (OUD).
They also discussed one of the supplements to CTN-0095, which tested a training to reduce stigma towards people with OUD among primary care clinicians.
Related protocols: CTN-0095

Background and aims: US regulatory changes allowed for additional methadone take-home doses following COVID-19 onset. How dispensing practices changed and which factors drove variation remains unexplored. We determined daily methadone dispensing trajectories over six months before and after regulatory changes due to COVID-19 using state sequence analysis and explored correlates.
Design: Retrospective chart review of electronic health records.
Settings: Nine opioid treatment programs (OTPs) across nine US states.
Participants: Adults initiating treatment in 2019 (n = 328) vs. initiating 1 month after the COVID-19 regulatory changes of March 2020 (n = 376).
Measurements: Type of daily methadone medication encounter (in-clinic, weekend/holiday take-home, take-home, missed dose, discontinued) based on OTP clinic; cohort (pre vs. post-COVID-19); and patient substance use, clinical and sociodemographic characteristics.
Findings: Following COVID-19 regulatory changes, allotted methadone take-home doses increased from 3.5% to 13.8% of total person-days in treatment within the first 6 months in care. Clinic site accounted for the greatest variation in methadone dispensing (6.2% and 9.5% of the variation of discrepancy between sequences pre- and post-COVID-19, respectively). People who co-use methamphetamine had a greater increase in take-homes than people who did not use methamphetamine (from 3.7% pre-pandemic to 21.2% post-pandemic vs. 3.5% to 12.5%) and higher discontinuation (average 3.6 vs. 4.7 months among people who did not use methamphetamine pre-COVID-19; average 3.3 vs. 4.6 months post-COVID-19). In the post-COVID-19 cohort, females had a higher proportion of missed doses (17.2% vs. 11.9%) than males. People experiencing houselessness had a higher proportion of missed doses (19% vs. 12.3%) and shorter stays (average 3.5 vs. 4.5 months) when compared with those with stable housing.
Conclusion: Daily methadone dispensing trajectories in the US both before and following COVID-19 regulatory changes appeared to depend more on the opioid treatment programs’ practices than individual patient characteristics or response to treatment.
Related protocols: CTN-0112

Aims: This study, supported by the CTN Ohio Valley Node, aimed to identify substance use disorder (SUD) patterns and their association with T2DM health outcomes among patients with type 2 diabetes and hypertension.
Methods: Researchers used latent class analysis on electronic health records from the MetroHealth System (Cleveland, Ohio) to obtain the target SUD groups: i) only tobacco (TUD), ii) tobacco and alcohol (TAUD), and iii) tobacco, alcohol, and at least one more substance (PSUD). A matching program with Mahalanobis distance within propensity score calipers created the matched control groups: no SUD (NSUD) for TUD and TUD for the other two SUD groups. The numbers of participants for the target-control groups were 8009 (TUD), 1672 (TAUD), and 642 (PSUD).
Results: TUD was significantly associated with T2DM complications. Compared to TUD, the TAUD group showed a significantly higher likelihood for all-cause mortality (adjusted odds ratio (aOR) = 1.46) but not for any of the T2DM complications. Compared to TUD, the PSUD group experienced a significantly higher risk for cerebrovascular accident (CVA) (aOR = 2.19), diabetic neuropathy (aOR = 1.76), myocardial infarction (MI) (aOR = 1.76), and all-cause mortality (aOR = 1.66).
Conclusions: The findings of increased risk associated with PSUDs may provide insights for better management of patients with T2DM and hypertension co-occurrence.
Primary care is a critical setting to provide care for the 75-79% of patients who have opioid use disorder (OUD) but do not receive medications for OUD. However, patient perceptions of primary care of OUD are not well understood. Patients completed surveys about their experience with opioid-related clinical decision support system (CDSS) printouts and OUD treatment in the first 7-9 months of implementation of an OUD-CDSS. Survey responses were presented overall and by reason for study eligibility. Of 277 patients completing surveys, 22% recalled seeing the printouts; of these, 85% said the printouts made them more comfortable discussion opioid risk. Of all respondents, half discussed opioids during their visit; of these, 84% felt conversations were conducted sensitively. Overall, 88% felt primary care was the right setting to discuss opioid risks. The opioid-related printouts and discussions were generally well-received, and patients felt primary care was a suitable setting for opioid-related care.
 Background: Opioid use disorder (OUD) remains a significant public health issue. Yet, few primary care clinicians (PCCs) screen for, diagnose, or treat OUD. Clinical decision support tools (CDS) integrated into the electronic health record improve process and outcome measures across a variety of conditions. We evaluated PCC perspectives on an OUD CDS tool (Opioid Wizard) deployed through a clinic-randomized trial.
Methods: This is a secondary analysis of CTN-0095, a trial evaluating the effectiveness of Opioid Wizard on OUD process and outcome measures. In short, 92 primary care clinics across three health systems were randomized to Opioid Wizard or usual care. PCCs completed online surveys pre- and 9-month post-Opioid Wizard’s go-live date. Survey items measured PCC self-reports on their confidence and ability to manage OUD, and for PCCs in Opioid Wizard clinics, perceptions about the tool. Generalized linear mixed models with Poisson distribution estimated change in survey response from baseline to follow-up within each treatment group (risk ratios) and in intervention relative to control clinics (ratio of risk ratios).
Results: 361 PCCs (n = 180 Opioid Wizard, n = 181 usual care, 63% female) answered at least one survey. Confidence in screening (RR 1.32, 95% CI 1.07, 1.62), diagnosing (RR 1.24, 95% CI 1.02, 1.50), and referring (RR 1.17, 95% CI 1.02, 1.34) patients for OUD care significantly increased in Opioid Wizard clinics only. Confidence in treating OUD with buprenorphine did not increase in either setting. Of 55 PCCs who used Opioid Wizard at least once, 80% agreed Opioid Wizard made tasks easier and 70% agreed using Opioid Wizard was time “well spent,” but only 44% were likely to recommend it to colleagues.
Conclusion: Opioid Wizard increased PCC confidence across a variety of OUD care measures yet enthusiasm for and use of the tool was limited. Efforts to increase Opioid Wizard use may improve OUD care measures.
Related protocols: CTN-0095
 Background: Most people with opioid use disorder (OUD) do not receive evidence-based treatment. To increase treatment rates, primary care clinics may choose to implement risk prediction tools available in the electronic health record (EHR) to identify patients with a high risk of OUD or overdose.
Objective: To externally validate Epic’s cognitive computing model to predict the Risk of Opioid Abuse or Overdose (referred to as the Opioid Risk Score; ORS) in three large integrated health systems.
Design: Prospective cohort study secondary to an ongoing clinical trial.
Participants: Patients (N = 704,764) aged 18-75 who had a primary care encounter during the study period (April 2021-December 2022) and did not have an OUD diagnosis at index.
Main measures: Data were extracted from the EHR. The index date was defined as the first date within the study period where the patient met eligibility criteria and had an ORS calculated by the EHR. The binary outcome variable was whether the patient was diagnosed with OUD or experienced an opioid overdose within 12 months of the index date.
Key results: Most patients were classified as low risk on ORS (99.6%). Few patients experienced an OUD diagnosis or overdose in the 12-month follow-up period (0.3%). The model correctly classified 185 of 2362 patients who experienced an event (sensitivity 0.0783, 95% CI 0.0675, 0.0892) and 699,926 of 702,406 patients who did not experience an event (specificity 0.9965, 95% CI 0.9963, 0.9966). Few patients with high ORS experienced the event (PPV 0.0694, 95% CI 0.0598, 0.0791). The model had excellent discrimination (c-statistic = 0.815) but was poorly calibrated, underestimating risk for patients who experienced the outcomes.
Conclusions: Epic’s ORS demonstrated excellent discrimination but very low sensitivity across three large integrated health systems. Health systems should exercise caution before implementing vendor risk prediction models without validating their use in their patient populations.
Related protocols: CTN-0095
 Objectives: Assessment and counseling are recommended for individuals with prenatal cannabis use. We examined characteristics that predict prenatal substance use assessment and counseling among individuals who screened positive for prenatal cannabis use in prenatal settings.
Methods: Electronic health record data from Kaiser Permanente Northern California’s Early Start perinatal substance use screening, assessment, and counseling program was used to identify individuals with =1 pregnancies positive for prenatal cannabis use. Outcomes included completion of a substance use assessment and among those assessed, attendance in Early Start counseling only or Addiction Medicine Recovery Services (AMRS) treatment. Predictors included demographics and past-year psychiatric and substance use disorder diagnoses evaluated with GEE multinomial logistic regression.
Results: The sample included 17,782 individuals with 20,398 pregnancies positive for cannabis use (1/2011-12/2021). Most pregnancies (80.3%) had an assessment. Individuals with Medicaid, anxiety, depression and tobacco use disorders, compared to those without, had higher odds and those with greater parity, older age (=35) and in later trimesters, had lower odds of assessment. Among 64% (n = 10,469) pregnancies needing intervention based on assessment, most (88%) attended Early Start counseling only or AMRS (with or without Early Start). Greater parity and later trimester assessment was associated with lower odds, while Medicaid was associated with higher odds of Early Start counseling. Nearly all diagnosed psychiatric and substance use disorders were associated with higher odds of AMRS treatment.
Conclusions: A comprehensive prenatal substance use program engaged most pregnant individuals with prenatal cannabis use in substance use assessment and counseling. Opportunities to improve care gaps remain.
Related protocols: CTN-0140
Background: Valid, single-item cannabis screens for the frequency of past-year use (SIS-C) can identify patients at risk for cannabis use disorder (CUD); however, the prevalence of CUD for patients who report varying frequencies of use in the clinical setting remains unexplored.
Objective: Compare clinical responses about the frequency of past-year cannabis use to typical use and CUD severity reported on a confidential survey.
Participants: Among adult patients in an integrated health system who completed the SIS-C as part of routine care (3/28/2019-9/12/2019; n = 108,950), 5000 were selected for a confidential survey using stratified random sampling. Among 1688 respondents (34% response rate), 1589 who reported past-year cannabis use on the SIS-C were included.
Main measures: We compared patients with varying frequency of cannabis use on the SIS-C (< monthly, monthly, weekly, daily) to survey responses on the Composite International Diagnostic Interview Substance Abuse Module for CUD (any and moderate-severe CUD) and cannabis exposure measures (typical use per-week, per-day). Adjusted multinomial (categorical) and logistic regression (binary), weighted for population estimates, estimated the prevalence of outcomes across frequencies.
Key results: Patients were predominantly middle-aged (mean = 43.3 years [SD = 16.9]), male (51.8%), white (78.2%), non-Hispanic (94.0%), and commercially insured (68.9%). The prevalence of any and moderate-severe CUD increased with greater frequency of past-year cannabis use reported on the SIS-C (p-values < 0.001) and ranged from 12.7% (6.3-19.2%) and 0.9% (0.0-2.7%) for < monthly to 44.6% (41.4-47.7%) and 20.3% (17.8-22.9%) for daily use, respectively. Greater frequency of use on the SIS-C in the clinical setting corresponded with greater per-week and per-day use on the confidential survey.
Conclusions: Among patients who reported past-year cannabis use as part of routine screening, the prevalence of CUD and other cannabis exposure measures increased with greater frequency of cannabis use, underscoring the utility of brief cannabis screens for identifying patients at risk for CUD.
Related protocols: CTN-0077-Ot
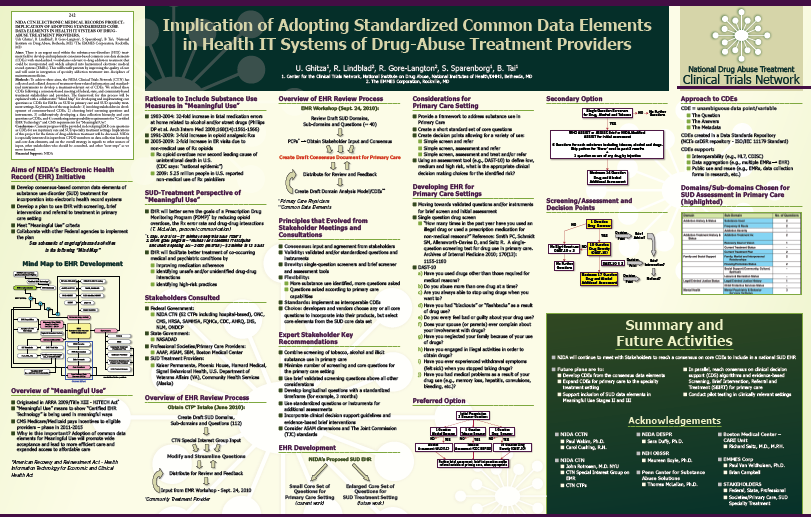 There is an urgent need within the substance-use-disorders (SUD) treatment field to develop and implement consensus-based common core data elements (CDEs) with standardized vocabularies relevant to drug addiction treatment that could be incorporated and widely adopted into harmonized electronic medical record systems (EMRs). This will benefit patients by improving the quality of care and will assist in integration of specialty addiction treatment into disciplines of mainstream medicine. To achieve these aims, the NIDA Clinical Trials Network (CTN) has collected and collated dozens of treatment-form-related information and standardized instruments to develop a treatment-relevant set of CDEs. These CDEs were refined following a consensus-based meeting of federal, state, and community-based treatment stakeholders and providers. This poster describes the collaborative “Mind Map” used for developing and implementing core questions as CDEs for EMRs on SUD in primary care and SUD specialty treatment settings. Current progress in developing EMR core questions as CDEs for use in those settings is also provided, as well as implications of this project for the future of drug abuse treatment. NIDA is especially interested in input from College on Problems of Drug Dependence (CPDD) members on data collection hierarchy and core data elements and on the overall strategy in regards to other sources of input, other stakeholders who should be consulted, and other “next steps” as this project moves forward.
 This population-based cross-sectional study, supported by CTN-0140, analyzed electronic health record data of pregnant individuals in an integrated health care delivery system in California to examine changes in prenatal cannabis use through self-report and urine toxicology testing during standard prenatal care between 2012 (n=33,546) and 2022 (n=43,415) and to test whether trends differed by race and ethnicity or age. The prevalence of prenatal cannabis use increased from 5.5% in 2012 to 9% in 2022, with similar increases by toxicology test and self-report. The increase in prevalence varied significantly across racial and ethnic and age groups, with the highest prevalence among Black individuals and those aged 13-24 across years. Although rates increased more slowly among groups with the highest prevalence of use, disparities persisted over time. These increases highlight the need to inform all pregnant individuals of the potential risks associated with prenatal cannabis use and connect them with nonjudgmental, culturally sensitive interventions, as needed.
Related protocols: CTN-0140
Opioid use disorder (OUD) and opioid dependence lead to significant morbidity and mortality, yet treatment retention, crucial for the effectiveness of medications like buprenorphine-naloxone, remains unpredictable. Our objective was to determine the predictability of 6-month retention in buprenorphine-naloxone treatment using electronic health record (EHR) data from diverse clinical settings and to identify key predictors.
This retrospective observational study, supported by CTN-0136, developed and validated machine learning-based clinical risk prediction models using EHR data. Data were sourced from Stanford University’s healthcare system and Holmusk’s NeuroBlu database, reflecting a wide range of healthcare settings. The study analyzed 1800 Stanford and 7957 NeuroBlu treatment encounters from 2008 to 2023 and from 2003 to 2023, respectively.
Measurements: Predict continuous prescription of buprenorphine-naloxone for at least 6 months, without a gap of more than 30 days. The performance of machine learning prediction models was assessed by area under receiver operating characteristic (ROC-AUC) analysis as well as precision, recall and calibration. To further validate our approach’s clinical applicability, we conducted two secondary analyses: a time-to-event analysis on a single site to estimate the duration of buprenorphine-naloxone treatment continuity evaluated by the C-index and a comparative evaluation against predictions made by three human clinical experts.
Attrition rates at 6 months were 58% (NeuroBlu) and 61% (Stanford). Prediction models trained and internally validated on NeuroBlu data achieved ROC-AUCs up to 75.8 (95% confidence interval [CI]=73.6–78.0). Addiction medicine specialists’ predictions show a ROC-AUC of 67.8 (95% CI=50.4–85.2). Time-to-event analysis on Stanford data indicated a median treatment retention time of 65 days, with random survival forest model achieving an average C-index of 65.9. The top predictor of treatment retention identified included the diagnosis of opioid dependence.
Conclusions: US patients with opioid use disorder or opioid dependence treated with buprenorphine-naloxone prescriptions appear to have a high (~60%) treatment attrition by 6 months. Machine learning models trained on diverse electronic health record datasets appear to be able to predict treatment continuity with accuracy comparable to that of clinical experts.
Related protocols: CTN-0136
 The purpose of this study, part of CTN-0102, was to investigate the prevalence of opioid use disorder (OUD) and medication treatment for OUD (MOUD) receipt in rural primary care settings and identify characteristics associated with MOUD among patients with OUD.
Researchers performed secondary analyses based on electronic health records of all adult patients who visited 1 of the 6 rural primary care clinic sites from October 2019 to January 2021. Mixed effects logistic regression was conducted to assess MOUD receipt (Y/N) in relation to patient characteristics (eg, demographics, other substance use disorders [SUDs], mental health disorders, and chronic pain) and the number of MOUD prescribers per clinic.
The prevalence of OUD varied from 0.7% to 8.2% (Mean [SD] = 3.3% [95% CI: 0.4, 6.1]) among 36,762 primary care patients across 6 clinic sites. Among 1,164 patients with OUD, on average 50.1% received MOUD (95% CI: 28.0, 72.3). Patients in clinics with more than 3 MOUD prescribers had more than 3 times the odds of receiving MOUD (OR = 3.42; 95% CI, 1.22-9.62) as those in clinics with fewer than 3 prescribers. MOUD was positively associated with younger age (18-30 [OR = 6.97; 95% CI, 3.37-14.42], 31-64 [OR = 5.03; 95% CI, 2.64-9.57], relative to those 65 and older), having other co-occurring SUDs (OR = 3.77; 95% CI, 2.57-5.52), being male (OR = 1.50; 95% CI, 1.12-2.01), and negatively associated with having chronic pain disorders (OR = 0.69; 95% CI, 0.50-0.94).
Conclusions: The prevalence of OUD and MOUD are high but vary considerably across rural primary care clinics; primary care MOUD prescribers play a key role on MOUD access in rural settings.
Related protocols: CTN-0102
 Medical and nonmedical cannabis use and cannabis use disorders (CUD) have increased with increasing cannabis legalization. However, the prevalence of CUD among primary care patients who use cannabis for medical or nonmedical reasons is unknown for patients in states with legal recreational use.
The goal of this study, a secondary analysis of data from CTN-0077-Ot, was to estimate the prevalence and severity of CUD among patients who report medical use only, nonmedical use only, and both reasons for cannabis use in a state with legal recreational use.
This cross-sectional survey study took place at an integrated health system in Washington State. Among 108 950 adult patients who completed routine cannabis screening from March 2019 to September 2019, 5000 were selected for a confidential cannabis survey using stratified random sampling for frequency of past-year cannabis use and race and ethnicity. Among 1688 respondents, 1463 reporting past 30-day cannabis use were included in the study.
Patient responses to the Composite International Diagnostic Interview-Substance Abuse Module for CUD, corresponding to Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition CUD severity (0-11 symptoms) were categorized as any CUD (=2 symptoms) and moderate to severe CUD (=4 symptoms). Adjusted analyses were weighted for survey stratification and nonresponse for primary care population estimates and compared prevalence of CUD across reasons for cannabis use.
Of 1463 included primary care patients (weighted mean [SD] age, 47.4 [16.8] years; 748 [weighted proportion, 61.9%] female) who used cannabis, 42.4% (95% CI, 31.2%-54.3%) reported medical use only, 25.1% (95% CI, 17.8%-34.2%) nonmedical use only, and 32.5% (95% CI, 25.3%-40.8%) both reasons for use. The prevalence of CUD was 21.3% (95% CI, 15.4%-28.6%) and did not vary across groups. The prevalence of moderate to severe CUD was 6.5% (95% CI, 5.0%-8.6%) and differed across groups: 1.3% (95% CI, 0.0%-2.8%) for medical use, 7.2% (95% CI, 3.9%-10.4%) for nonmedical use, and 7.5% (95% CI, 5.7%-9.4%) for both reasons for use (P=.01).
Conclusions: In this cross-sectional study of primary care patients in a state with legal recreational cannabis use, CUD was common among patients who used cannabis. Moderate to severe CUD was more prevalent among patients who reported any nonmedical use. These results underscore the importance of assessing patient cannabis use and CUD symptoms in medical settings.
Related protocols: CTN-0077-Ot
 Screening for substance use in rural primary care clinics faces unique challenges due to limited resources, high patient volumes, and multiple demands on providers. To explore the potential for electronic health record (EHR)-integrated screening in this context, researchers conducted an implementation feasibility study with a rural federally-qualified health center (FQHC) in Maine. This was an ancillary study to a NIDA Clinical Trials Network study of screening in urban primary care clinics (CTN-0062).
Researchers worked with stakeholders from three FQHC clinics to define and implement their optimal screening approach. Clinics used the Tobacco, Alcohol, Prescription Medication, and Other Substance (TAPS) Tool, completed on tablet computers in the waiting room, and results were immediately recorded in the EHR. Adult patients presenting for annual preventive care visits, but not those with other visit types, were eligible for screening. Data were analyzed for the first 12 months following implementation at each clinic to assess screening rates and prevalence of reported unhealthy substance use, and documentation of counseling using an EHR-integrated clinical decision support tool, for patients screening positive for moderate-high risk alcohol or drug use.
Screening was completed by 3749 patients, representing 93.4% of those with screening-eligible annual preventive care visits, and 18.5% of adult patients presenting for any type of primary care visit. Screening was self-administered in 92.9% of cases. The prevalence of moderate-high risk substance use detected on screening was 14.6% for tobacco, 30.4% for alcohol, 10.8% for cannabis, 0.3% for illicit drugs, and 0.6% for non-medical use of prescription drugs. Brief substance use counseling was documented for 17.4% of patients with any moderate-high risk alcohol or drug use.
Conclusions: Self-administered EHR-integrated screening was feasible to implement, and detected substantial alcohol, cannabis, and tobacco use in rural FQHC clinics. Counseling was documented for a minority of patients with moderate-high risk use, possibly indicating a need for better support of primary care providers in addressing substance use. There is potential to broaden the reach of screening by offering it at routine medical visits rather than restricting to annual preventive care visits, within these and other rural primary care clinics.
Related protocols: CTN-0062-Ot
International Classification of Diseases (ICD) diagnosis codes are often used in research to identify patients with opioid use disorder (OUD), but their accuracy for this purpose is not fully evaluated. This study describes application of ICD-10 diagnosis codes for opioid use, dependence and abuse from an electronic health record (EHR) data extraction using data from the clinics’ OUD patient registries and clinician/staff EHR entries.
The study, a secondary analysis of data gathered as part of CTN-0102, a feasibility study about the expansion of medication treatment for OUD in rural communities, used three data sources from each of 4 rural primary care clinics in Washington and Idaho: (1) a limited dataset extracted from the EHR, (2) a clinic-based registry of patients with OUD and (3) the clinician/staff interface of the EHR (e.g. progress notes, problem list). Data source one included records with six commonly applied ICD-10 codes for opioid use, dependence and abuse: F11.10 (opioid abuse, uncomplicated), F11.20 (opioid dependence, uncomplicated), F11.21 (opioid dependence, in remission), F11.23 (opioid dependence with withdrawal), F11.90 (opioid use, unspecified, uncomplicated) and F11.99 (opioid use, unspecified with unspecified opioid-induced disorder). Care coordinators used data sources two and three to categorize each patient identified in data source one: (1) confirmed OUD diagnosis, (2) may have OUD but no confirmed OUD diagnosis, (3) chronic pain with no evidence of OUD and (4) no evidence for OUD or chronic pain.
Analysis found that F11.10, F11.21 and F11.99 were applied most frequently to patients who had clinical diagnoses of OUD (64%, 89% and 79%, respectively). F11.20, F11.23 and F11.90 were applied to patients who had a diagnostic mix of OUD and chronic pain without OUD. The four clinics applied codes inconsistently.
Conclusions: This study found three ICD-10 diagnosis codes (F11.10 [opioid abuse, uncomplicated], F11.21 [opioid dependence, in remission], F11.99 [opioid use, unspecified with unspecified opioid-induced disorder]) that were used more consistently for patients with OUD and others (F11.20 [opioid dependence, uncomplicated], F11.23 [opioid dependence with withdrawal], F11.90 [opioid use, unspecified, uncomplicated]) that were applied to a mix of patients with OUD and patients with chronic pain and no evidence of OUD. Lack of uniform application of ICD diagnosis codes for patients with OUD makes it challenging to use diagnosis code data from the EHR to identify a research population of persons with OUD. Given the richness of the EHR data, it is important to develop new approaches so that researchers can confidently incorporate ICD diagnosis codes in accurately identifying patients with OUD and characterizing their clinical care in their studies.
Related protocols: CTN-0102