Search the Library
NOTE: This is a new search platform (as of May 2026). If you do a search and don’t get the results you were expecting, please email us at ctnlib@uw.edu to let us know? (If possible, please share your exact search strategy. Thank you!)
Enter keywords and hit Enter (or click the magnifying glass) to search. You can then also select document type or subject/topic to narrow results further (or just use those for searching without a keyword). Results display below this search form.
Document types
Subjects
- CTN-#### format for protocols (CTN-0001, e.g.)
- “exact phrase” (if phrase is not found, it will return results that contain all terms
- word1 NOT word2
- word1 word2 (finds both words)
- Click title to access full-text
- “Show details” reveals abstract & other info
- Checkboxes select items for copy/pasting or printing
- Need help getting a copy of a journal article?
Email ctnlib@uw.edu
Search results

The PATHS toolkit, a product of CTN-0080, offers evidence-based educational resources about the use of medication to treat opioid use disorder (OUD) during and after pregnancy. Resources include an introductory video, a range of printable downloads (flyers, discussion guide, factsheets, posters, and a workbook), and social media downloads to make dissemination of the tools easy and effective.
The toolkit is available in English and Spanish, and also includes a version culturally tailored for American Indian/Alaska Native communities.

Methadone is an essential tool for addressing opioid use disorder, especially with the prevalence of high-potency synthetic opioids in the drug supply. The current care delivery model in the United States with siloed methadone clinics has many limitations. Legislation has been proposed to expand access to methadone to office-based settings with pharmacy dispensing. Even with legal and regulatory changes, there are many practical barriers to implementation which include insurance coverage and patient cost, prior authorizations, and stocking of methadone.
Practical steps for clinicians and policymakers to take to overcome these barriers include ensuring insurance coverage for methadone, removing methadone from the algorithms that limit the amount of controlled substances pharmacies can order, and obtaining concentrated methadone formulations.
Related protocols: CTN-0131

Background and aims: US regulatory changes allowed for additional methadone take-home doses following COVID-19 onset. How dispensing practices changed and which factors drove variation remains unexplored. We determined daily methadone dispensing trajectories over six months before and after regulatory changes due to COVID-19 using state sequence analysis and explored correlates.
Design: Retrospective chart review of electronic health records.
Settings: Nine opioid treatment programs (OTPs) across nine US states.
Participants: Adults initiating treatment in 2019 (n = 328) vs. initiating 1 month after the COVID-19 regulatory changes of March 2020 (n = 376).
Measurements: Type of daily methadone medication encounter (in-clinic, weekend/holiday take-home, take-home, missed dose, discontinued) based on OTP clinic; cohort (pre vs. post-COVID-19); and patient substance use, clinical and sociodemographic characteristics.
Findings: Following COVID-19 regulatory changes, allotted methadone take-home doses increased from 3.5% to 13.8% of total person-days in treatment within the first 6 months in care. Clinic site accounted for the greatest variation in methadone dispensing (6.2% and 9.5% of the variation of discrepancy between sequences pre- and post-COVID-19, respectively). People who co-use methamphetamine had a greater increase in take-homes than people who did not use methamphetamine (from 3.7% pre-pandemic to 21.2% post-pandemic vs. 3.5% to 12.5%) and higher discontinuation (average 3.6 vs. 4.7 months among people who did not use methamphetamine pre-COVID-19; average 3.3 vs. 4.6 months post-COVID-19). In the post-COVID-19 cohort, females had a higher proportion of missed doses (17.2% vs. 11.9%) than males. People experiencing houselessness had a higher proportion of missed doses (19% vs. 12.3%) and shorter stays (average 3.5 vs. 4.5 months) when compared with those with stable housing.
Conclusion: Daily methadone dispensing trajectories in the US both before and following COVID-19 regulatory changes appeared to depend more on the opioid treatment programs’ practices than individual patient characteristics or response to treatment.
Related protocols: CTN-0112
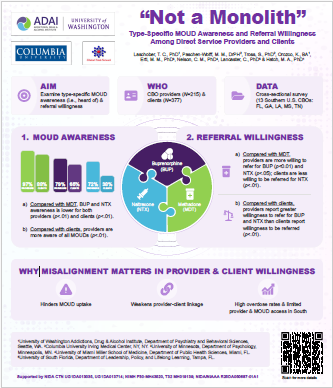
Poster describing a study that examined type-specific medications for opioid use disorder (MOUD) awareness (i.e., heard of) and referral willingness among CBO providers and clients. The data was acquired via cross-sectional survey of 13 Southern U.S. CBOs in FL, GA, LA, MS, and TN. Analysis revealed that compared with methadone, buprenorphine and naltrexone awareness is lower for both providers and clients, though providers are more aware of all types of MOUD than clients. Additionally, providers report greater willingness to refer for buprenorphine and naltrexone than clients report willingness to be referred (especially for naltrexone).
This type of misalignment can hinder MOUD uptake, weaken provider-client linkage, and contribute to high overdose rates and limited provider and MOUD access in the South.
Related protocols: CTN-0082
 Medications for opioid use disorder (MOUD), such as methadone, buprenorphine, and extended-release naltrexone (XR-NTX), have been shown to reduce or eliminate opioid use and craving, protecting against opioid overdose and death. Stopping medication is associated with risk of relapse and potential overdose. Unsurprisingly, patients may desire to stop MOUD because of adverse effects, burden, or preference for recovery without medication, asking, “How long do I need to take medication?” Clinicians who treat OUD often encounter this uncomfortable risk-benefit discussion with patients who want to stop MOUD, hoping that the patients can do so successfully, while acknowledging the major risks. Prospective data are needed to inform those discussions. In designing one of the first clinical trials focused on MOUD discontinuation—the Discontinuation Phase of the Optimizing Retention, Duration, and Discontinuation Strategies for Opioid Use Disorder Pharmacotherapy (RDD) trial (NCT04464980)2—the investigators identified ethical issues that needed consideration in designing the study.
The authors of this Viewpoint are study investigators, including a social worker (S.E.P.) and 2 psychiatrists experienced with MOUD (R.D.W. and E.V.N.). In this Viewpoint, we describe those ethical challenges and our attendant solutions to inform the design of other studies of medication discontinuation, where discontinuing treatment could have grave consequences.
Related protocols: CTN-0100
 This study applied the Theory of Reasoned Action (TRA) and Theory of Planned Behavior (TPB) to assess predictors of willingness to use three medications (methadone, buprenorphine, naltrexone) for opioid use disorder (MOUD), among people who use opioids (PWUOs). A single assessment survey, with measures aligned to the TRA/TPB were administered to 235, majority male, predominately White, PWUOs attending syringe services programs (SSPs) in the Southeastern United States, administered as part of CTN-0082. Hierarchical multiple regressions were used to analyze predictors of willingness to take each type of MOUD.
Conclusions: Findings partially supported the TRA but not TPB, with positive attitudes associated with greater willingness to use all three types of MOUD: pinpointing to the value of SSPs as a low threshold hub for treatment engagement.
Related protocols: CTN-0082
 Background and Objectives: Tobacco smoking and alcohol use disorder (AUD) are highly prevalent among individuals receiving medication for opioid use disorder (MOUD) treatment, yet their combined impact on treatment outcomes remains underexplored. This study investigates the differences in clinical profiles and treatment outcomes based on smoking and AUD status among individuals initiating MOUD.
Methods: This secondary analysis utilized data from a multi-site randomized clinical trial (CTN-0027) evaluating the hepatotoxicity during 24 weeks of buprenorphine or methadone treatment. Participants were categorized into four groups based on baseline smoking and AUD status: Non-AUD/Non-smoker, Smoker Only, AUD Only, and AUD+Smoker. Clinical profiles and treatment outcomes were compared across groups.
Results: Among 973 participants (68.6% male, 70.5% White, mean age 37.5 years), 50% were Smoker Only, 16% AUD+Smoker, 8% AUD Only, and 27% Non-AUD/Non-smoker. Smoking prevalence was high (66%), while AUD prevalence was lower (24%). AUD+Smoker and AUD Only groups had significantly higher rates of additional substance use disorders (p < .01). However, treatment outcomes—measured by urinalysis results, retention, and completion—did not differ significantly across groups.
Discussion and Conclusions: Smoking and AUD status were not associated with poorer MOUD outcomes, but the high prevalence of smoking, and the clustering of additional substance use disorders among individuals with AUD suggest the need for integrated care. These findings support inclusion of adjunctive behavioral and public health interventions within MOUD programs.
Related protocols: CTN-0027
 This is the primary outcomes article for CTN-0095.
Nearly 727,000 individuals in the US died of opioid overdoses between 1999 and 2022. The current workforce of addiction medicine specialists is inadequate to address the scale of this crisis, and primary care clinicians (PCCs) do not feel sufficiently supported to treat opioid use disorder (OUD).
Objective: To evaluate whether an electronic health record–integrated clinical decision support system (CDSS) increases OUD diagnosis and treatment in primary care.
Design, Setting, and Participants: This pragmatic cluster randomized clinical trial was conducted from April 2021 to December 2023. Primary care clinics in 3 health systems in 4 US states were randomized to receive or not receive an electronic health record–integrated CDSS aimed at improving OUD diagnosis and treatment. Eligible patients were aged 18 to 75 years, visited a randomized clinic, and had an OUD diagnosis in the last 2 years, opioid overdose in the last 6 months, or risk score indicating high risk of OUD or opioid overdose. Data were analyzed from September 2023 to October 2024.
Interventions: The OUD CDSS provided personalized treatment recommendations to patients and PCCs in intervention clinics.
Main Outcomes and Measures: Primary outcomes were likelihood to receive (1) an OUD diagnosis (among high-risk patients without a baseline OUD diagnosis), (2) a naloxone prescription, or (3) a prescription of a medication for OUD (MOUD) or specialty referral, all within 30 days of first eligible (index) visit, and (4) days covered by a MOUD prescription in the 90 days after index.
Results: Among 10,891 patients meeting eligibility criteria, 5918 (54.3%) were female, and the mean (SD) age was 48.0 (13.9) years. There was no difference in OUD diagnoses within 30 days between groups. Patients in the intervention group had more naloxone orders (80 of 5538 [1.4%] vs 40 of 5353 [0.7%]; odds ratio, 1.76; 95% CI, 1.14-2.72) and orders for MOUDs or treatment referral (775 of 5538 [14.0%] vs 503 of 5353 [9.4%]; odds ratio, 1.48; 95% CI, 1.05-2.08) within 30 days. There were no differences in median (IQR) days covered by MOUD over 90 days postindex between intervention (84 [55-90] days) and usual care (83 [55-90] days; rate ratio, 1.00; 95% CI, 0.93-1.08) or in overdose or death rates during the intervention period.
Conclusions and Relevance: In this cluster randomized clinical trial, the intervention improved rates of naloxone orders and OUD treatment in primary care but did not affect days covered by a MOUD over 90 days postindex or overdose or death rates. These findings demonstrate an OUD CDSS can help increase access to OUD treatment in primary care.
Related protocols: CTN-0095
Aim: This study: (1) estimated the effect of early discontinuation of medication for opioid use disorder (MOUD) on overdose probability and (2) measured the relationship between patient characteristics and early discontinuation probability for each MOUD type.
Design, setting and participants: This was a retrospective cohort using electronic health record data from the US Veterans Healthcare Administration. Participants were veterans initiating MOUD with buprenorphine (BUP), methadone (MET) or extended-release naltrexone (XR-NTX) from fiscal years 2012-19. A total of 39 284 veterans met eligibility with 22 721 (57.8%) initiating BUP, 12 652 (32.2%) initiating MET and 3911 (10.0%) initiating XR-NTX.
Measurements: Measurements (1) determined whether the veteran experienced an overdose in the 365 days after MOUD initiation (primary) and (2) early discontinuation of MOUD, defined as discontinuation before 180 days (secondary). We assumed that unobserved patient characteristics would jointly influence the probability of discontinuation and overdose. and estimated the joint distribution with a bivariate probit model.
Findings: We found that 9.0% of BUP initiators who experienced an overdose above the predicted 3.9% had no veteran-discontinued BUP early; findings for XR-NTX were similar, with 12.2% of initiators overdosing above the predicted 4.5%, but this was statistically inconclusive. We found no relationship between early discontinuation and overdose for MET initiators, probably due to the high risk of both events. The patient characteristics included in our post-estimation exploratory analysis of early discontinuation varied by MOUD type, with between 14 (XR-NTX) and 25 (BUP) tested. The only characteristics with at least one level showing a statistically significant change in probability of early discontinuation for all three MOUD types were geography and prior-year exposure to psychotherapy, although direction and magnitude varied.
Conclusions: Early discontinuation of buprenorphine, and probably extended-release naltrexone, appears to be associated with a greater probability of experiencing a fatal or non-fatal overdose among US veterans receiving medication for opioid use disorder (MOUD); methadone does not show the same association. There is no consistent set of characteristics among early discontinuers by MOUD type.
Related protocols: CTN-0142
 Illicit stimulant use among individuals initiating medication for opioid use disorder (MOUD) has significantly increased over the past decade. Co-use of these substances is associated with increased risk of mortality as well as worse treatment outcomes. This study examines the potential predictive role of stimulant urinalysis result at baseline on treatment retention and opioid and stimulant use outcomes amongst individuals initiating MOUD treatment.
This is a cross-sectional secondary analysis of data from a multi-site randomized clinical trial (CTN-0027). A total of 1269 individuals were randomized to receive 24 weeks of buprenorphine (n=740) or methadone (n=529) treatment across nine sites. Multiple linear and logistic regressions were conducted to determine the impact of baseline stimulant urinalysis results on treatment retention, and stimulant and opioid use outcomes.
Individuals initiating MOUD with a stimulant negative urinalysis result at baseline submitted more negative stimulant and opioid urinalyses during treatment, were more likely to complete treatment, and had better outcomes at six-month follow-up, measured as negative urinalysis for stimulant, and opioid.
Conclusions: Baseline stimulant use is associated with worse MOUD treatment outcomes, underscoring the need for novel integrated interventions designed to address opioid and stimulant co-use.
Related protocols: CTN-0027
 Introduction: Understanding conditions in which interventions succeed or fail is critical. The PRimary care Opioid Use Disorders treatment (PROUD) trial, a cluster-randomized hybrid study, tested whether implementation of office-based addiction treatment supported by a nurse increased medication of OUD. Six health systems each provided two primary care (PC) clinics that were randomly assigned to implement the intervention or usual care. This secondary, exploratory study used an innovative mixed methods approach to understand contextual factors that consistently distinguished intervention clinics that increased OUD treatment from those that did not.
Methods: The study collected contextual information through field notes, health system debriefs, and nurse interviews. Rapid qualitative analysis using a template based on the Practical, Robust Implementation and Sustainability Model identified themes reflecting the external environment, recipients, and implementation infrastructure. The study used qualitative themes to create binary factors reflecting barriers and facilitators potentially critical to implementation success and assigned clinics a factor value of 1 if present and 0 if absent. Two clinic-level outcomes were defined: 1) significant increase in patient-years of OUD treatment from baseline to two-year follow-up; and 2) high rate of OUD treatment at two-year follow-up (=20 per 10,000 patient-years). Coincidence analysis, a cross-case configurational method, identified difference-makers for both OUD outcomes across intervention clinics.
Results: Qualitative analysis yielded 11 themes which were dichotomized and consolidated into 9 factors. Two factor values perfectly distinguished between intervention clinics with and without increased OUD treatment (outcome #1): (a) presence of strong support from PC staff and providers and (b) lack of OUD treatment in the community. Intervention clinics increased OUD treatment when either factor value was present; when both were absent, clinics did not increase treatment. Strong support from PC staff and providers was independently sufficient to achieve high rates of OUD treatment (outcome #2) while the absence of support explained low rates of treatment. Importantly, strong support from leadership was not sufficient for either outcome.
Conclusions: Strong support from staff and providers consistently differentiated between clinics with increased OUD treatment across both outcomes in the PROUD trial from those without. OUD programs should consider increasing support across clinic roles.
Related protocols: CTN-0074
 Rural primary care clinics can expand their medication treatment for opioid use disorder (MOUD) capacity by coordinating care with external telemedicine (TM) vendors specializing in addiction medicine. This study used mixed methods to identify factors that influence patient referrals from rural primary care clinics to TM vendors for MOUD.
Between July/August 2020 and January/February 2021, 582 patients with OUD were identified across six primary care sites; that included 68 referred to an external TM vendor to receive MOUD. Mixed effects logistic regression identified individual and site-level factors associated with being referred to the TM vendor. Clinic providers and staff participated in in-depth interviews and focus groups to discuss their considerations for referring patients to the TM vendor.
Patient referrals were positively associated with local household broadband coverage (OR=2.55, p<0.001) and negatively associated with local population density (OR=0.01, p=0.003) and the number of buprenorphine prescribers in the county (OR=0.85, p<0.001). Clinic personnel expressed appreciation for psychiatric expertise and the flexibility to access MOUD brought by the TM vendor. Perceived concerns about TM referral included a lack of trust with external providers, uncertainty about TM service quality, workflow delays, and patients’ technological and insurance challenges.
Conclusions: This study revealed several clinic-level factors that may potentially influence patient referral to TM vendor services for MOUD. To facilitate the referral process and utilization of TM vendors, efforts should be made to foster open communication and trust between clinic providers and TM vendors, streamline workflows, and improve Internet access for patients.
Related protocols: CTN-0102
 Objectives: Racial and ethnic differences in long-term outcomes associated with medications for opioid use disorder (MOUD) are poorly understood.
Methods: The present analyses were based on 751 participants with opioid use disorder (OUD) who were initially recruited from opioid treatment programs located in California, Connecticut, Oregon, Pennsylvania, and Washington and participated in a randomized controlled trial and at least one follow-up interview. 9.6% (n=72) of the participants self-identified as Non-Hispanic (NH) Black, 16.0% (n=120) Hispanic, and 74.4% (n=559) NH White. We tested racial and ethnic differences in psychiatric or social functioning, substance use and treatment participation.
Results: From the baseline to the end of follow-up interview, compared with NH White, Hispanic participants had a significantly greater proportion of months reporting any opioid use (45.5% vs. 32.5%, p<0.001) and a smaller proportion of months receiving any MOUD (47.7% vs. 58.1%; p<0.05), particularly receipt of buprenorphine treatment (8.3% vs. 14.9%; p<0.01). At the third follow-up interview, data from the Addiction Severity Index (ASI) indicated that Hispanic participants had greater severity in employment problems (0.72 vs. 0.58; p < 0.001), while Black participants had less severity in drug problems (0.11 vs. 0.16; p<0.05) compared to NH Whites.
Conclusions: The study found that Hispanic participants had higher rates of opioid use (heroin and prescription opioids), but few received MOUD (buprenorphine and methadone) during the follow-up period, which suggests that effective strategies are needed to increase access to MOUD among Hispanics. Additionally, addressing employment challenges might also help improve long-term outcomes for all populations with OUD.
Related protocols: CTN-0050
 Several large-scale, pragmatic clinical trials on opioid use disorder (OUD) have been completed in the National Drug Abuse Treatment Clinical Trials Network (CTN). However, the resulting data have not been harmonized between the studies to compare the patient characteristics. This paper provides lessons learned from a large-scale harmonization process that are critical for all biomedical researchers collecting new data and those tasked with combining datasets.
Researchers harmonized data from multiple domains from CTN-0027 (N = 1269), which compared methadone and buprenorphine at federally licensed methadone treatment programs; CTN-0030 (N = 653), which recruited patients who used predominantly prescription opioids and were treated with buprenorphine; and CTN-0051 (N = 570), which compared buprenorphine and extended-release naltrexone (XR-NTX) and recruited from inpatient treatment facilities. Patient-level data were harmonized and a total of 23 database tables, with meticulous documentation, covering more than 110 variables, along with three tables with “meta-data” about the study design and treatment arms, were created. Domains included: social and demographic characteristics, medical and psychiatric history, self-reported drug use details and urine drug screening results, withdrawal, and treatment drug details.
In this paper, the authors summarize the numerous issues with the organization and fidelity of the publicly available data which were noted and resolved, and present results on patient characteristics across the three trials and the harmonized domains, respectively. A systematic harmonization of OUD clinical trial data can be accomplished, despite heterogeneous data coding and classification procedures, by standardizing commonly assessed characteristics. Similar methods, embracing database normalization and/or “tidy” data, should be used for future datasets in other substance use disorder clinical trials.
Related protocols: CTN-0027, CTN-0030, CTN-0051
Background: Individuals with opioid use disorder have high rates of hospital admissions, which represent a critical opportunity to engage patients and initiate medications for opioid use disorder (MOUD). However, few patients receive MOUD and, even if MOUD is initiated in the hospital, patients may encounter barriers to continuing MOUD in the community.
Objective: Describe hospital providers’ experiences and perspectives to inform initiatives and policies that support hospital-based MOUD initiation and continuation in community treatment programs.
Design: As part of a broader implementation study focused on inpatient MOUD (NCT#04921787), we conducted semi-structured interviews with hospital providers.
Participants: Fifty-seven hospital providers from 12 community hospitals.
Approach: Thematic analysis examined an emergent topic on challenges transitioning patients to outpatient MOUD treatment and related impacts on MOUD initiation by inpatient providers.
Key results: Participants described structural barriers to transitioning hospitalized patients to continuing outpatient MOUD including (a) limited outpatient buprenorphine prescriber availability, (b) the siloed nature of addiction treatment, and (c) long wait times. As a result of observing these structural barriers, participants experienced a sense of futility that deterred them from initiating MOUD. Participants proposed strategies that could better support these patient transitions, including developing partnerships between hospitals and outpatient addiction treatment and supporting in-reach services from community providers.
Conclusions: We identified concerns about inadequate and inaccessible community-based care and transition pathways that discouraged hospital providers from prescribing MOUD. As hospital-based opioid treatment models continue to expand, programmatic and policy strategies to support inpatient transitions to outpatient addiction treatment are needed.
Related protocols: CTN-0098